

Quick Answer: SMILE or LASIK – which is better?
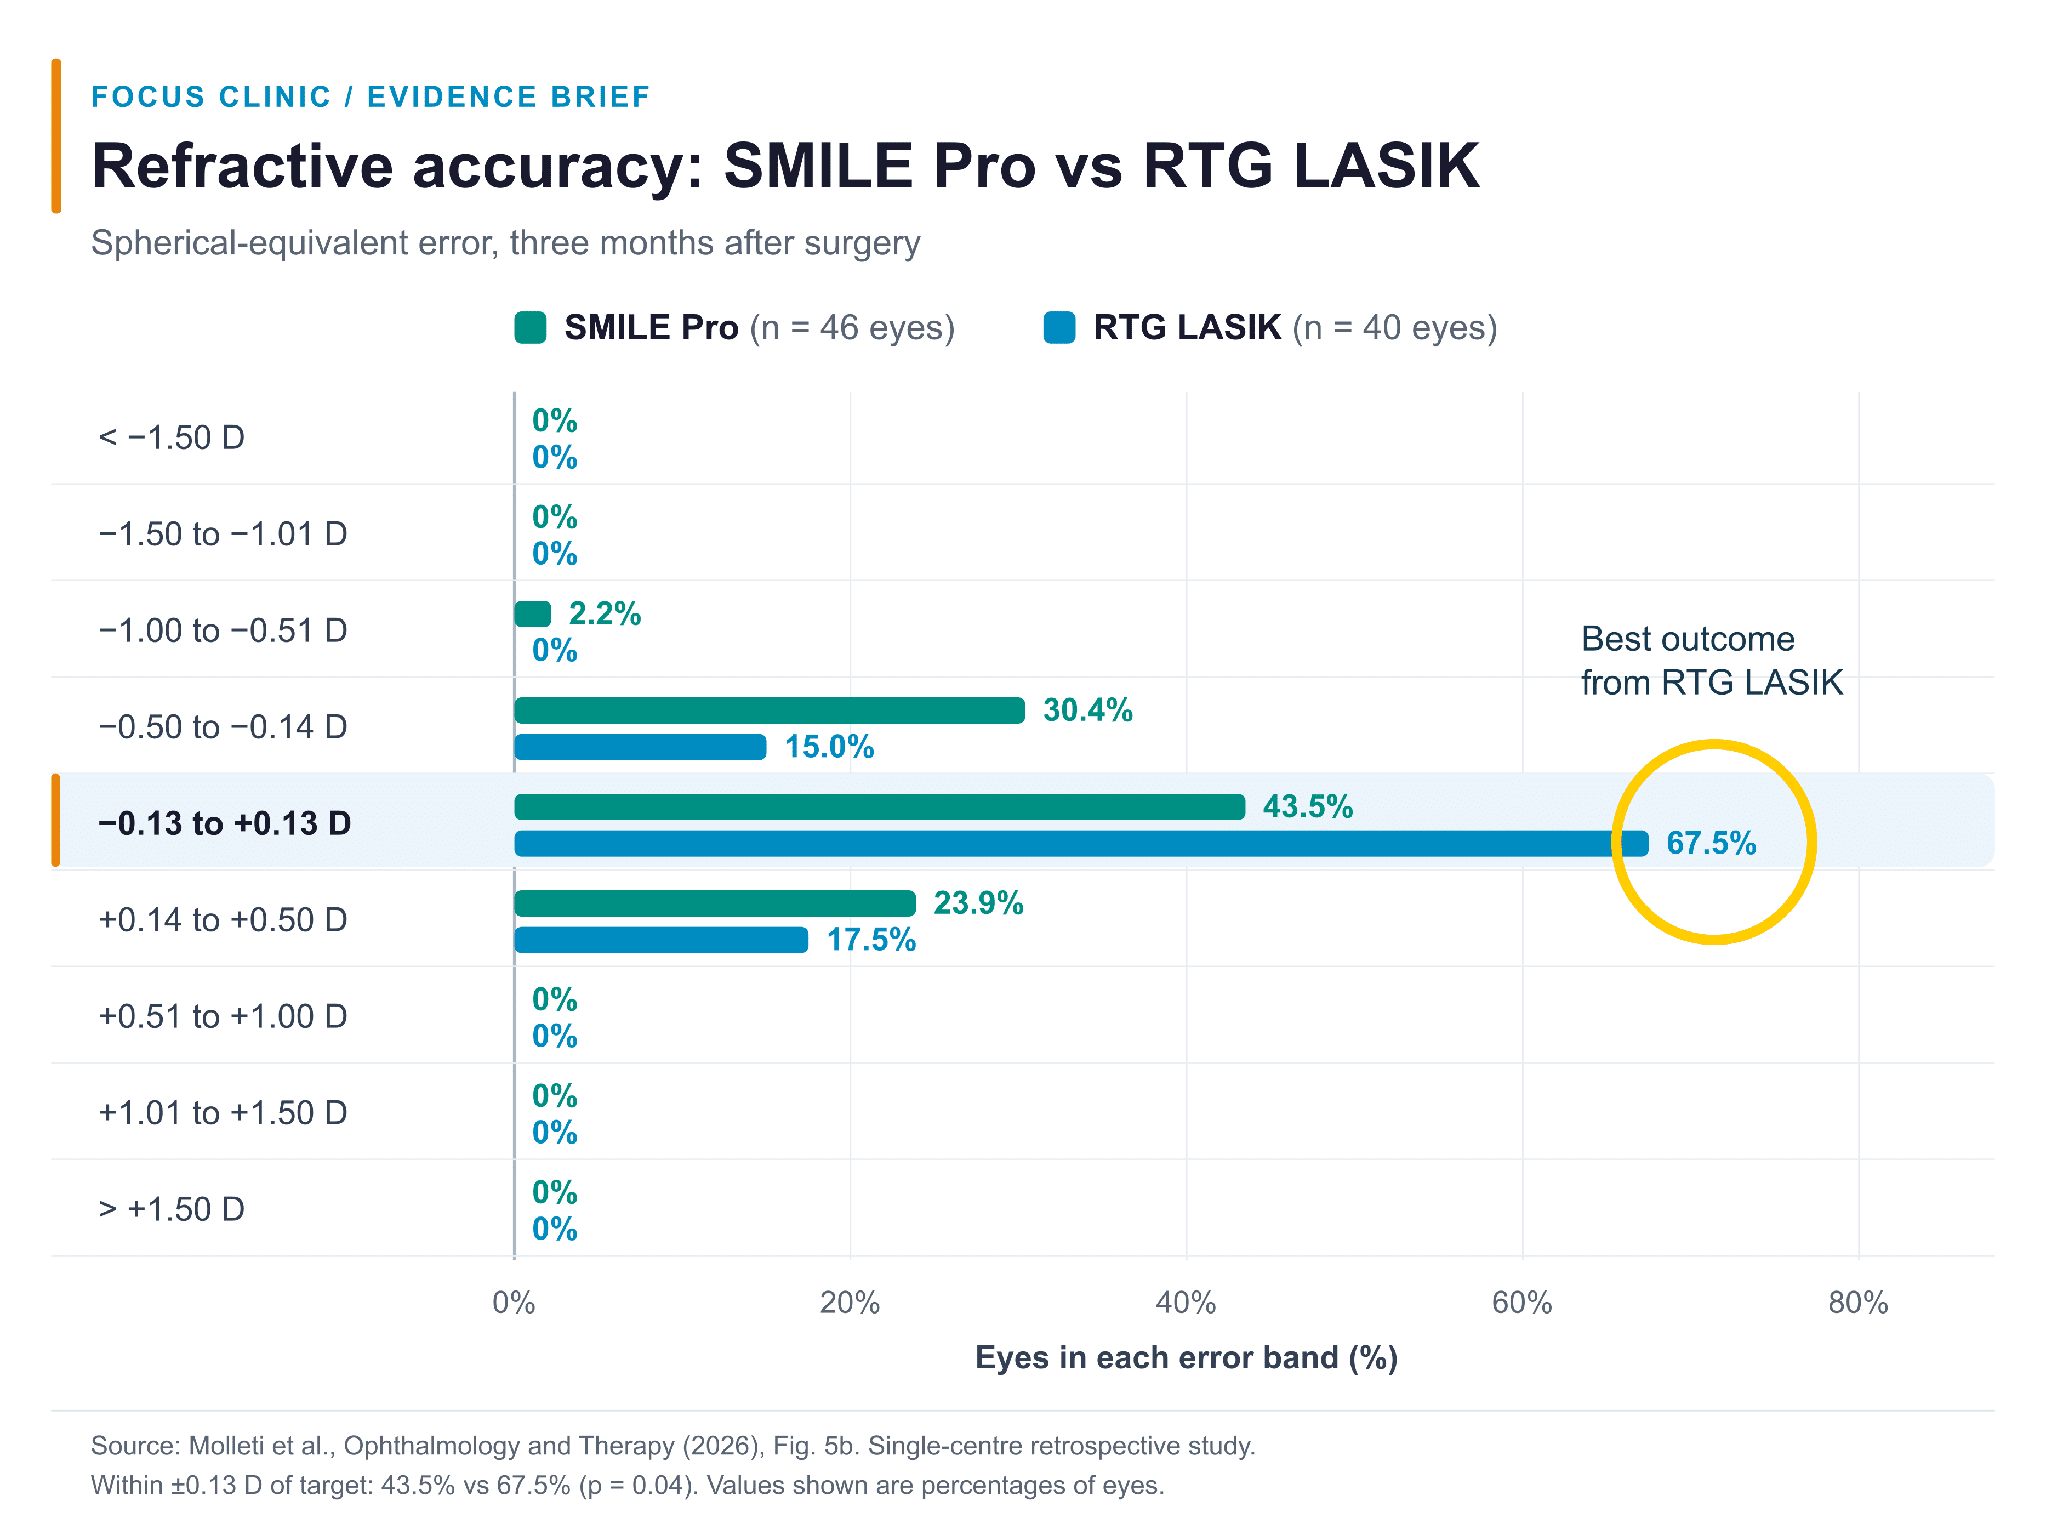
Previously, for most people with short-sightedness, LASIK and SMILE gave comparable vision. However, recent research suggests ray-tracing-guided (RTG) LASIK can give significantly better vision than SMILE Pro. [Molleti et al., 2026]
The direct answer is that the choice depends on your prescription, your eyes and your priorities – so let us go through the real differences one at a time.
For all statistics, higher is better
| Measure | SMILE Pro | RTG LASIK |
|---|---|---|
| 20/20 or better | 74% | 98% |
| Accuracy (±0.13 D) | 43.5% | 67.5% |
| Residual astigmatism (≤0.50 D) | 87% | 100% |
| Astigmatism axis error (<5°) | 56.7% | 71.4% |
| Residual astigmatism (≤0.25 D) | 56.5% | 90% |
Three-month results from a single-centre retrospective study (Molleti et al., 2026). The difference in astigmatism axis error under 5° was not statistically significant.
Those differences are in the details: LASIK treats a wider range (including long-sight and higher astigmatism), recovers faster, is easy to fine-tune later, and can be ray-tracing-guided (the latest evolution in customised laser eye surgery); SMILE is flapless and tends to cause slightly less dry eye in the first few months.
My default for the sharpest, most customisable result – especially with astigmatism or night-vision concerns – is ray-tracing-guided LASIK, with SMILE a strong flapless option for straightforward short-sight.
What is the difference between SMILE and LASIK?
LASIK creates a thin hinged flap in the cornea, lifts it, and reshapes the tissue underneath with an excimer laser. SMILE uses a single femtosecond laser to shape a small disc of tissue (a lenticule) inside the cornea and removes it through a keyhole incision, with no flap. Both reshape the cornea to correct your sight – they just get there differently.
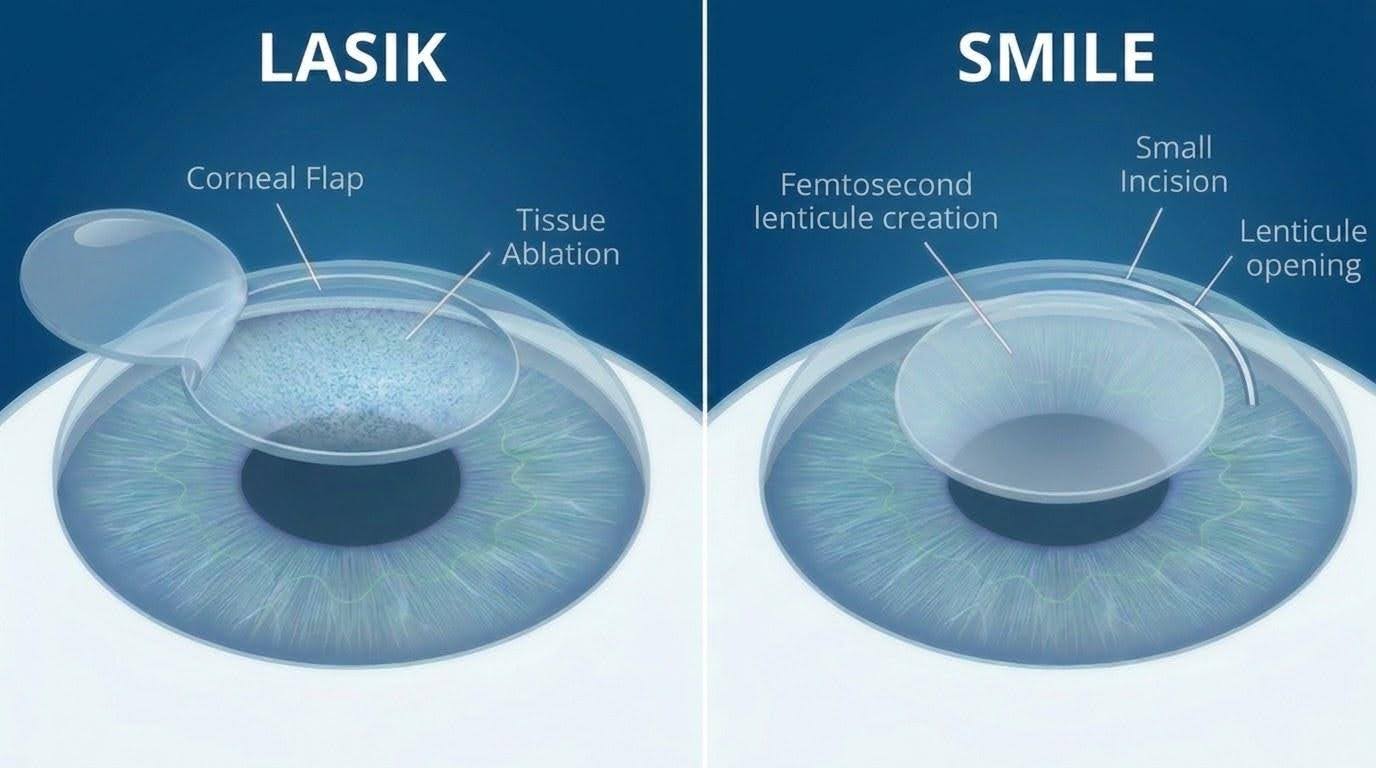
SMILE vs LASIK at a glance (individual suitability depends on your corneal scan)
| Feature | LASIK | SMILE |
|---|---|---|
| Incision | Thin hinged flap, lifted then replaced | Small keyhole incision, no flap |
| Lasers used | Femtosecond (flap) + excimer (reshaping) | Femtosecond only (one laser) |
| Corrects | Short-sight, long-sight and astigmatism | Short-sight and astigmatism (long-sight becoming available) |
| Ray-tracing available | Yes | No |
| Early dry eye | A little more common in the first months | Usually less in the first months |
| Visual recovery | Very fast, often the next day | Often days to weeks |
| Fine-tuning later | Straightforward (lift flap or surface laser) | Not with SMILE; needs surface laser or LASIK |
The headline difference is the flap. SMILE avoids one; LASIK uses one but, in return, treats a wider range and can be ray-tracing-guided. Neither is simply “better” – they suit different eyes and priorities.
Do SMILE and LASIK give the same visual results?
Not any more. LASIK wins. The confusion comes from the fact that there are different versions of LASIK. Conventional, older LASIK and SMILE gave comparable results for short-sight, and the published evidence is clear on that. But the newest option, ray-tracing-guided LASIK, gives better vision with greater accuracy than even the latest version of SMILE, called SMILE Pro.
The “they are the same” evidence is about conventional LASIK. A meta-analysis of high myopia found no significant difference in uncorrected vision or final prescription between SMILE and femtosecond LASIK (Fu et al., 2021).
An earlier meta-analysis of 27 studies and over 4,000 eyes reached the same conclusion – comparable efficacy, safety and predictability, with the aberration profile modestly favouring SMILE (Yan et al., 2017).
So if you are comparing SMILE with older, standard LASIK, expect a similar result.
Ray-tracing-guided LASIK is a different story. It is the newest laser method, and the only one that builds a digital twin of your eye and tailors the treatment to your individual optics – something SMILE cannot currently do.
In my experience of treating over a thousand ray-tracing-guided procedures, this is where LASIK genuinely pulls ahead.
Conventional LASIK, PRK and SMILE tend to increase higher-order aberrations – including spherical aberration, a driver of night vision issues – as the correction grows. SMILE does a bit better than standard LASIK for spherical aberration induction, but it still tends to increase. Ray-tracing treatment is designed to avoid that, with spherical aberration actually decreasing in the published data (He & Bala, 2023).
In a multi-centre study of the latest SMILE Pro (VISUMAX 800), 93.2% of eyes reached 20/20 or better at six months (Sekundo et al., 2025). In a real-world series of ray-tracing-guided LASIK for myopia, 100% of eyes reached 20/20 or better (He & Bala, 2023).
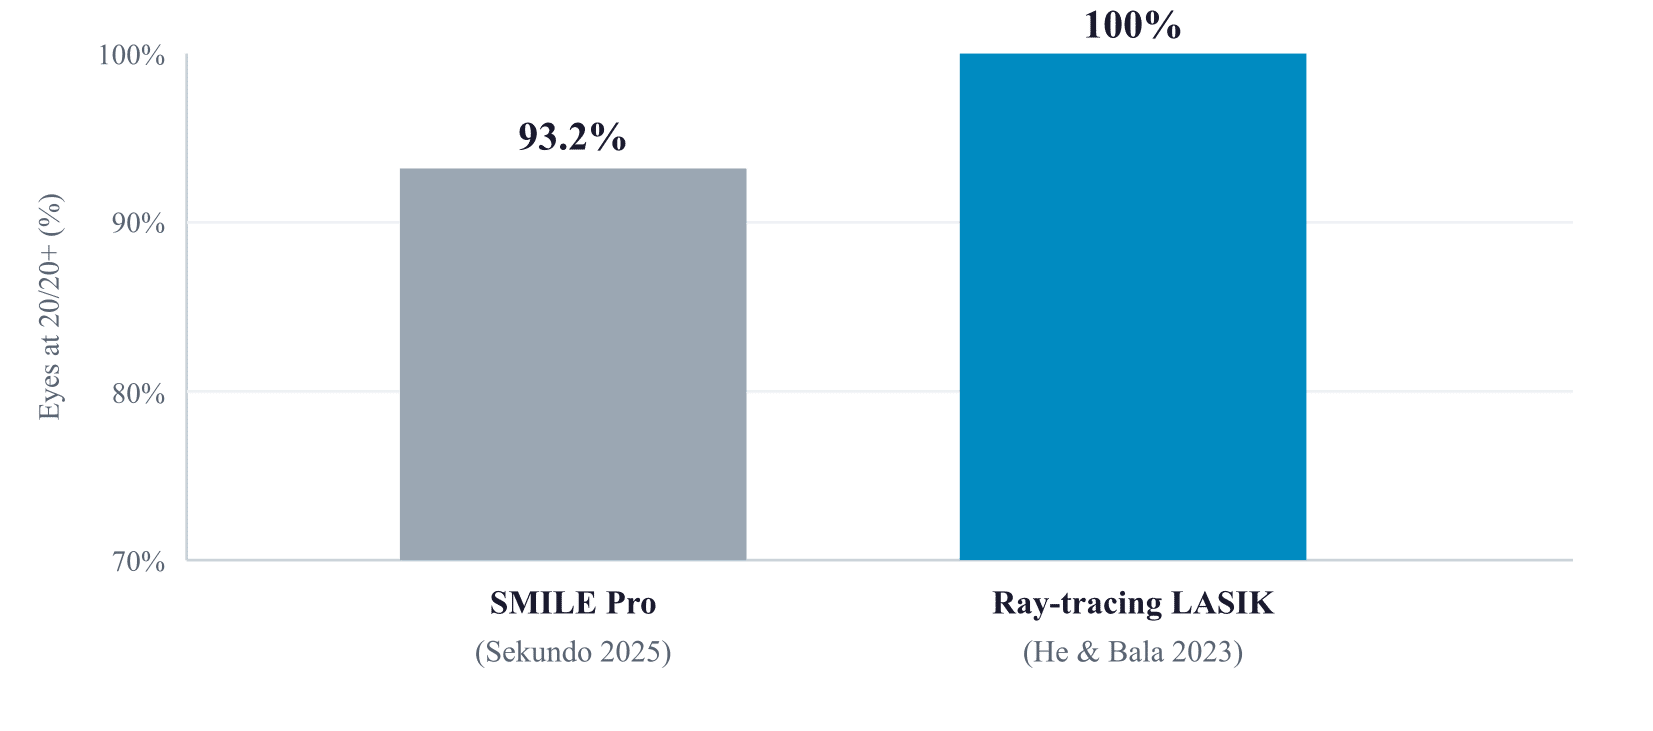
For everyday short-sight, SMILE and conventional LASIK are neck and neck. If you want the sharpest, most accurate result – or you have astigmatism – ray-tracing-guided LASIK has the edge, and that is my usual recommendation.
Which has less dry eye, SMILE or LASIK?
SMILE usually causes less dry eye in the first few months, because its lenticule incision size is significantly smaller than a LASIK flap, and so divides fewer corneal nerves. However, by around 6-12 months, the difference between the two largely evens out.
A meta-analysis found SMILE preserved tear break-up time and corneal nerve density better than femtosecond LASIK at 1 and 6 months, with a lower risk of post-operative dry eye during this early period. (Kobashi et al., Cornea, 2017.)
This fits the wider picture: a refractive-surgery meta-analysis found a significant early reduction in tear production and tear break-up time after LASIK, but only a non-significant reduction after SMILE (Sambhi et al., 2019). Randomised data show the gap narrows with time – less dry eye with SMILE in the first six months, but broadly the same as LASIK by twelve (Wang et al., 2015).
Either way, dry eye after modern laser surgery resolves for most people. A military study of US Army personnel found that, twelve months after surgery, 99.2% of LASIK and 95% of PRK patients were free of chronic dry eye (Bower et al., 2015).
In my own practice, I treat dry eye aggressively before I operate rather than hoping it settles afterwards. That means checking the tear film and eyelids at the consultation and dealing with any blepharitis, meibomian gland dysfunction or underlying dryness first – with lid care, anti-inflammatory drops and macrolide antibiotics, warm compresses and massage, omega-3s and lubricants – so the ocular surface is in the best possible shape on the day.
For patients who are prone to dryness, I also use punctal (tear) plugs: tiny inserts that keep your own tears on the eye for longer, which in my experience can reduce dry-eye symptoms by around 40%.
If you already have dry or sensitive eyes, SMILE’s gentler early nerve impact is a genuine point in its favour – but it is a short-term edge, not a permanent one, and good tear-film care matters more than the procedure name.
Is SMILE stronger for the cornea than LASIK?
SMILE’s genuine advantage here is that it is flapless, so there is no flap that could be dislodged by an injury later – useful if you play contact sports or have a job with a high risk of eye trauma. The claim that SMILE always leaves a biomechanically stronger cornea, though, is not fully supported.
Matched clinical and laboratory studies show that the residual stromal bed left beneath the treatment, not the preserved surface layer (which may no longer be under tension due to the volume removed by the lenticule), may be the main determinant of corneal stiffness – and by that measure SMILE is not automatically stronger than LASIK (Hashemi et al., 2023).
The early hope that SMILE’s biomechanics might make it a safer choice for borderline, ectasia-risk corneas has since been tested and not borne out, so SMILE should not be treated as the safer option for those eyes (Randleman, 2021). So the fair way to put it is this: SMILE removes the flap-related risks, which is a real, practical benefit, but “no flap” is not the same as “stronger cornea” (Kanellopoulos, 2018).
Choose SMILE for the flapless benefit if trauma risk is a real part of your life – not on the assumption that it makes the cornea inherently tougher. For most people, corneal strength is determined in both procedures by careful screening and leaving enough tissue in reserve.
Which is better for astigmatism, long-sight and higher prescriptions?
I prefer LASIK. SMILE mainly corrects short-sight and astigmatism, and tends to undercorrect higher degrees of astigmatism; long-sight treatment is only just becoming available on SMILE Pro, with not much published data so far. LASIK treats a fuller range. Ray-tracing-guided LASIK is available for short-sight and astigmatism and appears to be accurate even for higher prescriptions.
A vector analysis of SMILE for myopic astigmatism found a tendency to undercorrect in eyes with higher astigmatism (over 3.00 D), with lower safety and efficacy in that group. (Jabbarvand et al., Eur J Ophthalmol, 2022.)
For long-sight, the position is still emerging: SMILE Pro for hyperopia is only now becoming available and has very little published data behind it. On the current-generation laser it amounts to a single pilot study of 11 eyes, followed for three months, in which only 18.2% of eyes reached 20/20 unaided and the authors themselves call for larger studies with longer follow-up (Chung et al., 2026).
LASIK, by contrast, treats long-sight routinely. And when astigmatism is involved, the accuracy of the treatment plan matters most – which is exactly where ray-tracing-guided LASIK, tailored to your individual optics, has the edge.
If you have significant astigmatism, LASIK – ideally ray-tracing-guided – is usually the better choice. My own experience of ray-traced correction of astigmatism has been very impressive.
Can you have ray-tracing-guided treatment with SMILE?
No. Ray-tracing is available for LASIK (and PRK), not SMILE. This is the single biggest reason I most often recommend LASIK when a patient wants the most accurate, customised result.
In a study of ray-tracing-guided LASIK, 100% of eyes reached 20/20 or better and 98% of patients were satisfied, with no significant rise in objective visual-quality measures. (Yang et al., Clin Ophthalmol, 2026.)
If ray-tracing accuracy matters to you – for astigmatism, a demanding visual job, or night driving – that decides it in LASIK’s favour, because SMILE cannot offer it. One caveat: ray-tracing is currently for short-sight and astigmatism, not long-sight.
Clinical references
- Fu Y, Yin Y, Wu X, et al. Clinical outcomes after small-incision lenticule extraction versus femtosecond laser-assisted LASIK for high myopia: A meta-analysis. PLoS One. 2021;16(2):e0242059. doi.org/10.1371/journal.pone.0242059
- Yan H, Gong LY, Huang W, Peng YL. Clinical outcomes of small incision lenticule extraction versus femtosecond laser-assisted LASIK for myopia: a Meta-analysis. Int J Ophthalmol. 2017;10(9):1436-1445. doi.org/10.18240/ijo.2017.09.17
- Sekundo W, Chang JSM, Ganesh S, Hjortdal J, Wiltfang R. Keratorefractive Lenticule Extraction for Myopia and Myopic Astigmatism With the VISUMAX 800: 6-Month Outcomes of a Prospective Multi-center Post-market Clinical Follow-up Study. J Refract Surg. 2025;41(3):e264-e271. doi.org/10.3928/1081597X-20250204-03
- Kobashi H, Kamiya K, Shimizu K. Dry Eye After Small Incision Lenticule Extraction and Femtosecond Laser-Assisted LASIK: Meta-Analysis. Cornea. 2017;36(1):85-91. doi.org/10.1097/ICO.0000000000000999
- Sambhi RS, Sambhi GDS, Mather R, Malvankar-Mehta MS. Dry eye after refractive surgery: a meta-analysis. Can J Ophthalmol. 2020;55(2):99-106. doi.org/10.1016/j.jcjo.2019.07.005
- Wang B, Naidu RK, Chu R, Dai J, Qu X, Zhou H. Dry Eye Disease following Refractive Surgery: A 12-Month Follow-Up of SMILE versus FS-LASIK in High Myopia. J Ophthalmol. 2015;2015:132417. doi.org/10.1155/2015/132417
- Bower KS, Sia RK, Ryan DS, Mines MJ, Dartt DA. Chronic dry eye in photorefractive keratectomy and laser in situ keratomileusis: Manifestations, incidence, and predictive factors. J Cataract Refract Surg. 2015;41(12):2624-2634. doi.org/10.1016/j.jcrs.2015.06.037
- Hashemi H, Roberts CJ, Elsheikh A, Mehravaran S, Panahi P, Asgari S. Corneal Biomechanics After SMILE, Femtosecond-Assisted LASIK, and Photorefractive Keratectomy: A Matched Comparison Study. Transl Vis Sci Technol. 2023;12(3):12. doi.org/10.1167/tvst.12.3.12
- Kanellopoulos AJ. Comparison of corneal biomechanics after myopic small-incision lenticule extraction compared to LASIK: an ex vivo study. Clin Ophthalmol. 2018;12:237-245. doi.org/10.2147/OPTH.S153509
- Randleman JB. Ectasia After SMILE, Revisited. J Refract Surg. 2021;37(12):798-799. doi.org/10.3928/1081597X-20211025-01
- Jabbarvand M, Khodaparast M, Moravvej Z, et al. Vector analysis of moderate to high myopic astigmatism after small-incision lenticule extraction (SMILE): 12-month follow-up. Eur J Ophthalmol. 2022;32(6):3312-3320. doi.org/10.1177/11206721221080821
- Chung HY, Chung YT, Kim BK, You IC. Early Clinical Outcome of Hyperopic Small Incision Lenticule Extraction (SMILE) Using the VisuMax 800 in South Korea: A Pilot Study. Korean J Ophthalmol. 2026;40(3):280-291. doi.org/10.3341/kjo.2026.0008
- He G, Bala C. Ray-tracing-guided myopic LASIK: real-world clinical outcomes. J Cataract Refract Surg. 2023;49(11):1140-1146. doi.org/10.1097/j.jcrs.0000000000001286
- Yang L, Luo L, Zhang Y, et al. Ray-Tracing-Guided Femtosecond LASIK: Refractive Outcomes, Visual Quality and Patient Satisfaction. Clin Ophthalmol. 2026;20:574112. doi.org/10.2147/OPTH.S574112
- Molleti S, et al. Initial Visual and Refractive Outcomes of Ray-Tracing-Guided LASIK (WaveLight Plus) Versus KLEx (SMILE Pro). Ophthalmol Ther. 2026;15:3401-3419. doi.org/10.1007/s40123-026-01475-1
This article is for general information and does not replace a personal consultation. Suitability for LASIK or SMILE can only be confirmed after a full eye assessment and corneal scan.